
The main blood tests for women's hormones are FSH and LH, oestradiol, progesterone, testosterone with SHBG, prolactin, and the thyroid tests TSH and free T4. Several of these change through the menstrual cycle, so the day you give your sample matters when the result is read. This guide explains what each test shows, when to take it, and how results are used for PMOS (formerly PCOS), perimenopause, thyroid problems, heavy periods and fertility.
What do women's hormones do?
The glands behind the hormones on a women's blood test, and how they work together.
Four of the hormones on a typical women's blood test come from one gland, the pituitary. It makes FSH (follicle stimulating hormone) and LH (luteinising hormone), which control the ovaries. It makes TSH (thyroid stimulating hormone), which tells the thyroid to make thyroid hormones, with a feedback loop that limits how hard the thyroid is pushed. And it makes prolactin.
Think of the pituitary as the manager, and the ovaries and thyroid as the teams doing the work. A blood test can show both sides: the instruction and the response.
The ovaries make oestradiol, the strongest of the three natural oestrogens. Before the menopause, that's where most of a woman's oestradiol comes from. In the second half of the cycle, a small structure in the ovary called the corpus luteum releases progesterone. If there's no pregnancy, it breaks down and progesterone falls.
Which tests check women's hormones?
Each of the main women's hormone tests, explained in a sentence or two.
The descriptions below draw on the Society for Endocrinology's patient pages, NHS laboratory guidance, NICE and the 2023 international guideline on PCOS.
FSH (follicle stimulating hormone)
Made by the pituitary gland to control the ovaries. It rises around the menopause, as the brain tries harder to stimulate the ovaries.
LH (luteinising hormone)
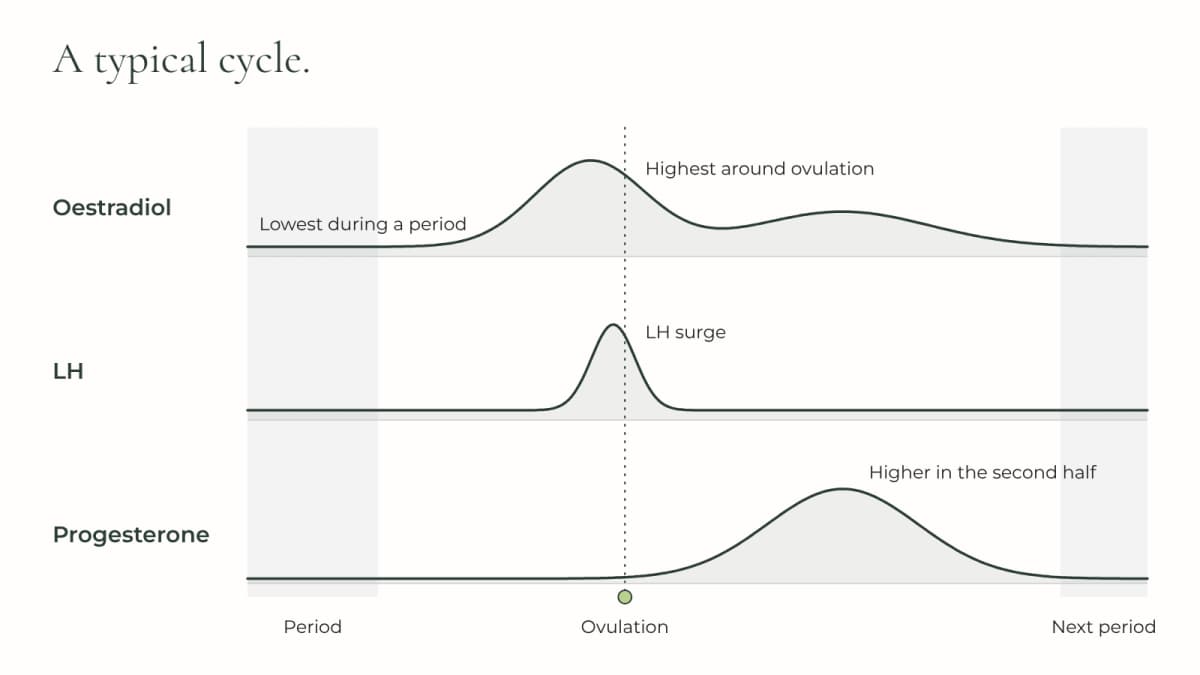
Also made by the pituitary. A surge of LH in the middle of the cycle triggers the release of an egg.
Oestradiol
The strongest natural oestrogen, made mostly in the ovaries before the menopause. It's highest around ovulation and lowest during a period.
Progesterone
Released mainly in the second half of the cycle. Measured about 7 days before your next period, it's used to check whether you've ovulated.
Testosterone
An androgen, a type of hormone usually linked with men. Guidelines use total and free testosterone to check for high androgen levels in women.
SHBG (sex hormone binding globulin)
A protein that carries testosterone and other sex hormones in the blood. It's read alongside testosterone.
Free androgen index (FAI)
An estimate of free testosterone, used when checking for high androgen levels.
Prolactin
Made mainly in the pituitary. Too much can disturb the cycle and cause unwanted breast milk.
TSH and free T4
TSH tells the thyroid to make its hormones. Free T4 is a thyroid hormone, added when TSH is outside the range.
AMH (anti-Müllerian hormone)
Used in fertility care to predict how the ovaries will respond to IVF stimulation. In adults, it can stand in for a scan when checking for polycystic ovaries.
Our Female Hormone Profile puts all of these except progesterone and AMH on one panel: FSH, LH, oestradiol, prolactin, total testosterone, SHBG, the free androgen index, TSH and free T4. For how testosterone is read in men, see our men's health guide.
Related test
Female Hormone Profile
9 markers for a broad look at women's hormones: FSH, LH, oestradiol, prolactin, testosterone with SHBG and FAI, and thyroid TSH and free T4.
Base price. Clinic appointments cost extra.
When in your cycle to test
Why the day of your cycle matters, which hormones to test when, and how contraception changes results.
FSH, LH and oestradiol are tested early in the cycle, and progesterone about a week before your next period.
The NHS puts the average cycle at around 28 days, and says regular cycles anywhere from 21 to 35 days are normal. In most women, ovulation happens around 10 to 16 days before the next period. That's why "day 14" only fits a 28 day cycle.
Early in the cycle: FSH, LH and oestradiol
Oestradiol is at its lowest during a period and highest around ovulation, so the day matters when it's read. One NHS laboratory recommends taking FSH samples on days 1 to 5 of the cycle. Our hormone test instructions ask for a morning sample on days 2 to 5.
About a week before your period: progesterone
Progesterone is measured about 7 days before your next expected period, to check whether ovulation has happened. In a 28 day cycle, that's day 21. For women having fertility investigations whose cycles are irregular, NICE says the test may need to be done later, for example on day 28 of a 35 day cycle, and repeated weekly until the next period starts.
Contraception and your results
Hormonal contraception changes some results.
SHBG and testosterone. A 2014 review of 42 studies in 1,495 healthy women aged 18 to 40 found SHBG rose while women took the combined pill, and free testosterone fell, by about 61% on average.
Androgens. The 2023 PCOS guideline says androgen results are very hard to read in women taking the combined pill.
FSH. NICE says not to use an FSH test to identify menopause in people using combined oestrogen and progestogen contraception or high dose progestogen.
If you use hormonal contraception, note it when you test. Whoever reads your results can then take it into account.
Can blood tests show PMOS (PCOS)?
The new name, the two of three rule, and what blood tests add.
Partly. Blood tests can show high androgens, one of the three features doctors look for, and help rule out conditions that look similar. In adults, a raised AMH can also stand in for a scan.
First, the name. In May 2026, The Lancet published a global consensus renaming polycystic ovary syndrome (PCOS) as polyendocrine metabolic ovarian syndrome, or PMOS. The NHS now uses the new name. The criteria for the condition haven't changed, and both names will be used side by side for 3 years.
The 2023 international guideline puts it at 10% to 13% of women worldwide, using the Rotterdam criteria. The NHS lists symptoms including irregular periods, excess hair growth or hair loss, weight gain, difficulty getting pregnant, and oily skin and acne. It also points out that these symptoms are common and can have many causes.
The two of three rule
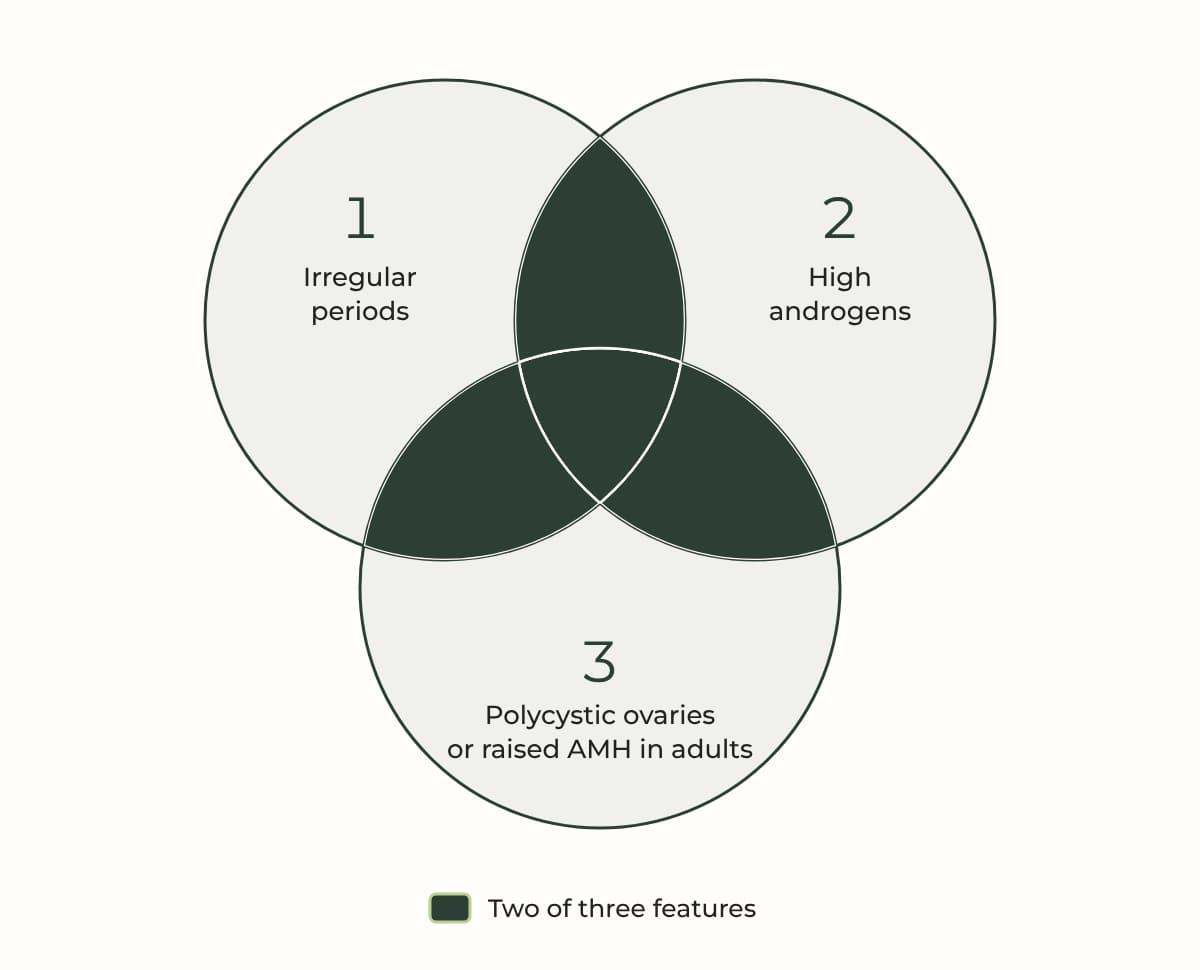
Doctors look for two of three features, once other causes have been ruled out.
Irregular periods or problems with ovulation. For adults, from 3 years after periods start, the guideline defines irregular cycles as shorter than 21 days, longer than 35 days, or fewer than 8 a year.
Signs of high androgens, on a blood test or as symptoms such as excess hair.
Polycystic ovaries on a scan or, in adults, a raised AMH.
In adults who already have irregular periods and high androgens, an ultrasound isn't needed.
What blood tests add
Testosterone. To check for high androgens, the guideline recommends total and free testosterone. Free testosterone can be estimated with the free androgen index. If testosterone isn't raised, androstenedione and DHEAS could be considered, though they are less specific.
AMH. In adults, AMH can be used instead of an ultrasound to look for polycystic ovaries. It shouldn't yet be used this way in teenagers, or as a single test for the condition.
Ruling out lookalikes. Conditions that can look similar are ruled out with tests including TSH (thyroid), prolactin and 17-hydroxyprogesterone.
LH and FSH. An LH to FSH ratio is often raised in PMOS but can be normal. It isn't one of the three features.
Insulin. The guideline says the insulin tests available in clinics are of limited use and doesn't recommend them in routine care.
The Female Hormone Profile above covers the androgen tests (total testosterone, SHBG and the free androgen index), plus two of the tests used to rule out lookalikes, TSH and prolactin.
Can blood tests confirm menopause or perimenopause?
What NICE says about FSH tests at each age, and what the menopause does to your hormones.
NICE says to consider an FSH blood test to help confirm menopause in two groups: women aged 40 to 45 with menopause symptoms, including a change in their periods, and women under 40 in whom menopause is suspected.
In the UK, menopause happens at 51 on average, usually between 45 and 55. As the ovaries run out of follicles, oestrogen falls, and FSH rises as the brain tries harder to stimulate the ovaries. The NHS describes menopause as no period for 12 months when you're not using hormonal contraception, and perimenopause as when periods become irregular.
NICE's menopause guideline, updated in 2024, sets out the role of blood tests by age.
Under 40
NICE says premature ovarian insufficiency is confirmed from symptoms, such as no or infrequent periods, plus raised FSH on 2 samples taken 4 to 6 weeks apart, "not on the basis of a single blood test".
40 to 45
NICE suggests considering an FSH test to confirm menopause in women with symptoms, including a change in their periods.
45 or over
NICE says otherwise healthy women with symptoms can be recognised as perimenopausal or menopausal from their symptoms and periods, without a laboratory test.
For women aged 45 or over, NICE says not to use AMH, inhibin A, inhibin B, oestradiol, antral follicle count or ovarian volume to identify perimenopause or menopause.
NICE also asks clinicians to be aware that in menopausal women, symptoms of thyroid problems may be mistaken for the menopause.
Our Perimenopause Hormone Check (Ages 40 to 45) matches NICE's 40 to 45 age band for FSH testing. It includes FSH, plus TSH and free T4 for the thyroid.
Related test
Perimenopause Hormone Check (Ages 40 to 45)
5 markers for women aged 40 to 45 with changing periods: FSH, LH and oestradiol, plus thyroid TSH and free T4, as thyroid symptoms can feel similar.
Base price. Clinic appointments cost extra.
Should women check their thyroid?
Why thyroid problems matter more for women, how the NHS tests, and what antibodies add.
Women are far more likely than men to develop an underactive thyroid. The Whickham study followed 2,779 adults in north east England for 20 years and counted new cases each year.
About 4 in 1,000
women a year developed an underactive thyroid in the Whickham study
0.6 in 1,000
men a year in the same study
In the UK, the main cause of an underactive thyroid is Hashimoto's disease, where the immune system attacks the thyroid. It's most common in women and usually starts between the ages of 30 and 50, though anyone can get an underactive thyroid.
How the NHS tests
When a thyroid problem is suspected in an adult, NICE suggests TSH alone as the first test. Free T4 is added if TSH is above the range, and free T4 and free T3 if it's below. Many of our panels measure all three together.
What antibodies add
In the Whickham study, women who had both a raised TSH and positive thyroid antibodies at the start were much more likely to have developed an underactive thyroid 20 years later. NICE suggests considering a thyroid peroxidase antibody (TPOAb) test for adults with a TSH above the range.
One raised result
NICE's guideline committee noted that in adults with a TSH between 5 and 10 mU/litre, the result might return to the range without treatment in around half of people. Thyroid results can also be abnormal in people who are acutely unwell with an illness that isn't thyroid related. A repeat test lets you see whether a raised result has settled.
Thyroid checks also feature in our article on the blood tests worth tracking once you turn 40. Our Thyroid Profile with Antibodies measures TSH, free T4, free T3, total T4 and both thyroid antibodies, TPOAb and TgAb.
Related test
Thyroid Profile with Antibodies
6 thyroid markers: TSH, free and total T4, free T3, and the TPO and thyroglobulin antibodies, for a fuller picture of how your thyroid is doing.
Base price. Clinic appointments cost extra.
Heavy periods, iron and tiredness
How heavy periods link to low iron, and which blood tests show it.
The NHS names heavy periods and pregnancy as very common causes of iron deficiency anaemia. British Society of Gastroenterology guidance says menstrual blood loss is commonly the cause in women before the menopause, and gives these figures for the developed world.
5% to 12%
of otherwise healthy women before the menopause have iron deficiency anaemia
2% to 5%
of adult men and women after the menopause
The NHS says you may have heavy periods if you:
need to change pads or tampons every 1 to 2 hours, or use two at once
have periods lasting more than 7 days
pass blood clots larger than about 2.5cm
bleed through to your clothes or bedding
avoid daily activities because of your period
feel tired or short of breath a lot
Causes include PMOS, fibroids, endometriosis, conditions that make you bleed more easily, and some medicines.
Anaemia means a haemoglobin result below the normal range for your age and sex. Symptoms of iron deficiency anaemia can include tiredness and lack of energy, shortness of breath, heart palpitations and paler skin.
The tests that show it
For heavy periods, NICE recommends a full blood count for every woman. A GP will usually do this test to check whether your red blood cell level is normal. NICE also says not to test ferritin routinely for heavy periods, and not to do female hormone tests, or thyroid tests unless there are other signs of thyroid disease.
Ferritin answers a different question: how much iron you have in reserve. The level in your blood is used as a measure of how much iron your body has stored, so think of it as your iron savings account. British Society of Gastroenterology guidance calls ferritin the single most useful marker of iron deficiency anaemia. Ferritin also rises with inflammation, so it can look normal in someone who is short of iron. Other tests, such as transferrin saturation, can help when that's suspected.
Serum iron on its own is a poor guide. It accounts for only about 1% of the body's iron, and it swings widely during the day and from one day to the next. That's why iron, TIBC (total iron binding capacity) and transferrin saturation are read together with ferritin. A raised TIBC with a low transferrin saturation points to iron deficiency.
Ferritin cut offs also vary. One NHS laboratory guide uses a lower threshold for women than the British Society of Gastroenterology does, so read your result against your lab's range. Our article on what a workplace blood test can and can't tell you covers reading a single result.
Our Advanced Tiredness and Fatigue Blood Test includes a full blood count, ferritin, iron, TIBC and transferrin saturation, plus folate, active B12, vitamin D, TSH and free T4.
Related test
Advanced Tiredness and Fatigue Blood Test
26 markers for tiredness that won't shift: full blood count, iron, active B12, folate, vitamin D, thyroid, HbA1c and inflammation in one report.
What does AMH show about fertility?
What an AMH test shows, where it's used, and what it can't predict.
An AMH (anti-Müllerian hormone) test helps predict how your ovaries will respond to stimulation in IVF. NICE says to use AMH, or an ultrasound count of follicles called the antral follicle count, for exactly that. It also says to use them to help counsel people about their chance of a live birth after assisted conception. AMH has a second use in PMOS: in adults, a raised AMH can stand in for a scan.
What AMH doesn't do is predict natural conception. NICE says not to use AMH to predict pregnancy through natural conception, and says age is the first predictor of the overall chance of pregnancy. A US study of 750 women aged 30 to 44 who had just started trying to conceive, with no history of infertility, agrees. Those with a low AMH were no less likely to conceive within 6 or 12 menstrual cycles than those with a normal AMH, and the same was true of a high FSH.
So AMH earns its keep in fertility treatment. If you're planning IVF, it's one of the measures NICE uses to predict how your ovaries will respond. If you're trying naturally, the progesterone test described above is the one used to check whether you've ovulated.
Missed periods, stress and training
The common reasons periods change or stop, and the blood tests used to look for the cause.
When periods stop, blood tests help find out why. After a pregnancy test, the Society for Endocrinology lists FSH, LH, oestrogen, prolactin, androgens and thyroid function among the blood tests used to look for the cause.
The NHS calls periods irregular when the gap between them is less than 21 days or more than 35. Its list of common causes includes stress and anxiety, losing or gaining a lot of weight, exercising too much and some hormonal contraception, and PMOS and thyroid problems can cause irregular periods too.
The Society for Endocrinology says the most common causes of periods stopping are recent stress, a change in weight, excessive dieting or exercise, or illness. It calls three or more months without a period, in someone whose periods were regular, secondary amenorrhoea. People with amenorrhoea are at risk of thin bones (osteoporosis).
Low energy availability means eating too little energy for the amount of exercise you do. The International Olympic Committee's consensus says it can lead to a range of health and performance problems in female and male athletes, which it calls relative energy deficiency in sport (REDs). Our article on why athletes need to read their blood tests differently goes further.
What about stress hormones? The adrenal glands make cortisol, the body's natural steroid. It helps regulate metabolism and is released during the stress response to illness. DHEA, also made mainly in the adrenal glands, travels in the blood mostly as DHEAS. Its production peaks in the 20s and gradually falls into old age.
The NHS gives clear advice on when to see a GP about your periods.
See a GP if you've missed 3 periods in a row, your periods last longer than 7 days, you bleed between periods or after sex, heavy periods are affecting your life, or your periods are irregular and you're struggling to get pregnant. Any bleeding from the vagina after the menopause should be checked by a GP, even if it's only a small amount or has only happened once.
How testing works with us
How samples are taken, how results reach you, and who checks them.
From sample to explanation, it takes five steps.
Choose how to give a sample
Depending on the test, you can use a home finger prick kit, have a home visit, or come to our Hull clinic.
Time it right
Follow your test's instructions on cycle day and time of day, and note any hormonal contraception you use.
Checked by our team
Every result is checked by our team before it's released.
Results in your portal
Results usually come back within 24 to 48 hours, and arrive through a secure email link to your own results portal.
Each marker explained
Your explanation covers what each marker measures and what it can and can't show.
Some more advanced panels take longer. Our tests are processed by a UKAS accredited laboratory (ISO 15189). We serve customers in England only. For more on how private testing works, see our guide to private diagnostics.
Common questions
Quick answers to common questions about women's hormone tests.
When in my cycle should I have a hormone test?
FSH, LH and oestradiol are tested early in the cycle; our instructions say days 2 to 5. Progesterone is measured about 7 days before your next expected period, which is day 21 only in a 28 day cycle.
Does the pill affect hormone blood test results?
Yes, for some tests. The combined pill raises SHBG, lowers free testosterone and makes androgen results very hard to read. Tell whoever reads your results what you take.
Do I need to fast for a female hormone test?
Our instructions ask for a morning sample, before eating, for tests that include testosterone. Other tests may have their own instructions. Our article Do you really need to fast before a blood test? explains which tests need it.
Can a blood test show a hormone imbalance?
A blood test shows the level of each hormone on the day, against your lab's reference range, and what it means depends on your cycle day and any contraception. For PMOS, perimenopause and thyroid problems, results sit alongside your symptoms in a doctor's assessment.
What's the difference between total and free testosterone?
Total testosterone counts all of it. Some is carried by a protein called SHBG, and the widely used view is that only the unbound, free part acts on the body, though scientists still debate this.
How often should women have a hormone test?
The guidelines cited here don't set a routine interval for healthy women. A test is most useful when you have a question to answer, such as changing periods, new symptoms or fertility plans. Repeating it later lets you compare against your own earlier result, so you can see how things change.
Know where you stand
Home finger-prick kits, nurse visits and clinic appointments, with your results explained.
Browse all tests
Daniel SnowWritten by · BSc (Hons), PGCE
This guide is for general information only and is not medical advice. If you have symptoms or concerns, speak with a qualified clinician.